
2.2 Outpatient Care
Outpatient services occur in a facility or setting where there is no need for an overnight stay. The types of procedures and tests offered might include wellness and prevention services, such as annual exams; diagnostic services, such as lab tests and imaging scans; treatment, such as day surgeries or chemotherapy; and rehabilitation, such as physical therapy or addiction treatment. Because no overnight stay is involved, outpatient services usually cost less. Some facilities specialize in one kind of treatment or procedure, such as an orthopedic surgery center, although many can be provided in one place. Three types of outpatient care include primary care, ambulatory surgical care, and urgent care.
2.2.1 Primary Care
I. Description
Primary care is the entry point into the healthcare system and is one of the most utilized outpatient services. Primary care clinics are the point of delivery of individual care based on care over time and are not disease-oriented but focus on preventive and sick visits. Primary care providers see patients who do not require immediate medical care for life-threatening conditions.
Primary care services cover a range of prevention, wellness, and treatment for common illnesses. Primary care providers include doctors, nurses, nurse practitioners, and physician assistants. They often maintain long-term relationships with you and advise and treat you on a range of health-related issues. They may also coordinate your care with specialists.
The four pillars of primary care, represented in Figure 2-1, are (Starfield, 1998):
- A patient’s first contact with the healthcare system
- Continuity of care over time
- Comprehensiveness (i.e., concern for the whole patient rather than a disease or part of the patient)
- Coordination of care
Figure 2-1
The Four Pillars of Primary Care
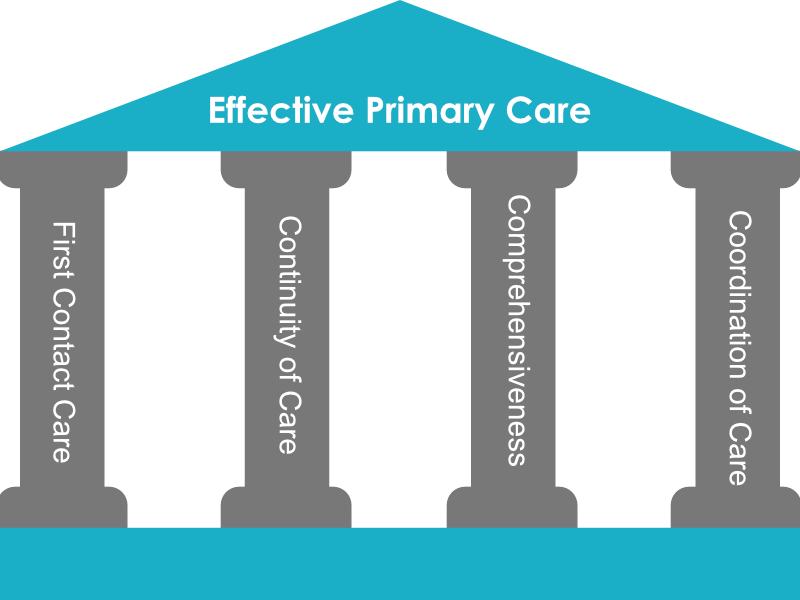
(Starfield, 1998)
II. Venues
There are several venues for the delivery of primary care. A major one is the private clinic of physicians. Another primary care venue is the public or non-profit community health center, which provides access to primary care for low-income, uninsured, and minority populations (Bodenheimer & Pham, 2010). Other government settings include clinics for the military (such as those run by the Veterans Health Administration), prisons, the Indian Health Service, and centers for migrants and the homeless (Bodenheimer & Pham, 2010). Urban public and teaching hospitals may also have outpatient clinics for primary care services, typically serving underserved populations (Bodenheimer & Pham, 2010). In addition, many integrated care systems, such as Kaiser Permanente and Geisinger Health System, provide primary care as part of their integrated systems, which cover primary, specialty, emergency, and hospital care (Bodenheimer & Pham, 2010). Finally, workplace wellness programs and retail clinics provide some primary care services by providing screening, health promotion, and basic prevention services (Baicker et al., 2010; RAND Corporation, 2010).
Retail clinics, also known as convenient care clinics, are healthcare clinics located within retail settings and are designed to provide convenient access to care for minor illnesses and injuries and other basic health needs. These clinics are commonly staffed by nurse practitioners and physician assistants and may provide vaccinations, health screenings, physical examinations, and management of selected chronic conditions. CVS MinuteClinic is an example of this model, with clinics located in CVS Pharmacy and select Target stores (CVS Pharmacy, n.d.). The retail healthcare market continues to evolve as organizations expand, modify, or discontinue different models of care. Amazon expanded its healthcare presence through its acquisition of One Medical in 2023, while Walmart closed all 51 of its Walmart Health centers in 2024 (Amazon, 2023; Walmart, 2024).
The following two models of care are being employed to increase efficiencies in primary care delivery: patient-centered medical homes and accountable care organizations.
- Patient-centered medical homes (PCMHs) have several characteristics that should positively impact the delivery of primary care: (1) each patient has an ongoing relationship with a primary care provider; (2) the primary care provider directs the medical team; (3) the primary care provider has responsibility for caring for all the patient’s health needs through all stages of the patient’s life; (4) patient care is coordinated across all healthcare settings; (5) services are safe, evidence-based and of high quality, with patients actively participating in decision-making; (6) patients have access to care; (7) payment systems recognize the added value of PCMHs (Rittenhouse et al., 2011). The Affordable Care Act has promoted PCMHs by paying state Medicaid programs to shift patients into medical homes, funding new PCMH models of care, and supporting the information technology needed for care coordination in PCMHs (Hoff et al., 2012).
- Accountable care organizations (ACOs) are groups of physicians, hospitals, and other healthcare providers that work together to provide coordinated, high-quality care. ACOs are accountable for both the quality and cost of care provided to a defined patient population. The Medicare Shared Savings Program was established under the Patient Protection and Affordable Care Act and began in 2012. Under the program, participating ACOs may share in savings when they provide high-quality care while spending healthcare dollars more efficiently. Some ACO arrangements also require organizations to share in financial losses when spending exceeds established benchmarks (CMS, 2026a). ACOs are now an established component of Medicare’s value-based care strategy. In 2026, 511 ACOs participate in the Medicare Shared Savings Program, serving 12.6 million people with Traditional Medicare. Across CMS accountable care initiatives, an estimated 14.3 million Medicare beneficiaries receive care coordinated through ACOs (CMS, 2026a).
2.2.2 Ambulatory Surgery Centers
Improvements in surgical equipment, techniques, anesthesia, and postoperative care have allowed an increasing number of procedures to be performed safely on an outpatient basis. Ambulatory surgery can be performed in hospital outpatient departments or freestanding ambulatory surgical centers (ASCs). ASCs allow patients to undergo selected procedures without an overnight hospital stay and generally return home the same day. In 2024, approximately 6,400 ASCs provided services to 3.4 million fee-for-service Medicare beneficiaries. The number of Medicare-certified ASCs increased by 2.2% from 2023 to 2024, and the volume of ASC surgical procedures per fee-for-service Medicare beneficiary increased by 3.5% during the same period (Medicare Payment Advisory Commission [MedPAC], 2026). The types and complexity of procedures performed in ambulatory settings also continue to expand, including increasing use of ASCs for hip, knee, and shoulder replacement procedures (MedPAC, 2026). Not all surgeries or patients are appropriate for the ambulatory setting. The appropriate site of surgery depends on factors such as the type and complexity of the procedure, the patient’s health and risk factors, and the level of postoperative monitoring and care required.
More complex surgeries are increasingly being performed on an outpatient basis as advances in surgical techniques, anesthesia, and postoperative care reduce the invasiveness of procedures and recovery time. Knee replacement is a good example of this shift. In 2024, 86% of knee replacement procedures were performed either in a hospital outpatient setting or an ambulatory surgical center (CMS, 2026b). Hip replacement procedures have also increasingly shifted outside the inpatient setting (CMS, 2026b).
Compared with hospital outpatient departments, ASCs may offer advantages such as greater scheduling flexibility and lower costs for selected procedures (Munnich & Parente, 2014; Plotzke & Courtemanche, 2011). Research has also found that ASCs can provide selected procedures at lower cost with outcomes comparable to hospital outpatient settings (Chukmaitov et al., 2008; Hollenbeck et al., 2015; Munnich & Parente, 2014). However, concerns associated with ASCs include physician self-referral and patient selection, particularly whether ASCs are more likely to serve healthier and more profitable patients while patients with greater medical complexity receive care in hospital outpatient settings (Hollenbeck et al., 2010; Koenig & Gu, 2013; Plotzke & Courtemanche, 2011).
2.2.3 Urgent Care
Outpatient clinics and urgent care facilities often serve as alternative places to receive healthcare when individuals cannot get to a hospital. During a public health emergency, these settings may see an increase in the number of patients they treat.
Urgent care is provided outside the emergency department setting in urgent care centers (UCCs) that provide care on a walk-in basis, have extended hours into the evening Monday to Friday and at least one day over the weekend, and have on-site laboratories and radiology (American College of Emergency Physicians [ACEP], 2017; Le & Hsia, 2016). The scope of services in these centers is broader than those in many primary care offices or retail clinics and falls somewhere between that of a primary care practitioner’s office and an emergency department (ACEP, 2017; Le & Hsia, 2016). Services focus on acute episodic care including care for minor illnesses and emergencies such as upper respiratory infections, urinary tract infections, backaches, sprains, strains, lacerations, burns, and minor fractures (Corwin et al., 2016; Stoimenoff & Dunn, 2018). Medical care is typically performed by primary care physicians, APRNs, and PAs (ACEP, 2017; Le & Hsia, 2016). UCCs have expanded rapidly over the past few years (Stoimenoff & Dunn, 2018). This expansion has been in response to difficulties in seeing primary care practitioners on an urgent basis and after hours, high emergency department costs, and long emergency department waiting times (Stoimenoff & Dunn, 2018; Villasenor & Krouse, 2016). The ability to get same-day test results and medications also makes them popular. Some individuals use UCCs because they do not have a regular source of primary care (Stoimenoff & Dunn, 2018). Studies have shown that areas with more urgent care alternatives to emergency departments have lower emergency department use for low acuity diagnoses (Llovera et al., 2019).
Knowledge Check
Match each statement to the correct center to complete the sentences.
