
3.2 Private Health Insurance
3.2.1 Employer-Sponsored (Group) Insurance
Employer-sponsored insurance remains the most common source of health coverage for working-age Americans. In 2025, 55% of workers were covered by a health plan offered by their employer (KFF, 2025). The employer-sponsored insurance journey is similar to that of hospitals and physicians. Initially, medical insurance was what we categorize as catastrophic indemnity insurance, with copays ranging from 10%-20%. Catastrophic indemnity insurance pays only for significant expenses over a certain amount, such as hospitalization, similar to automobile insurance. Gradually, more services were offered as part of medical insurance until any service, including preventive care, might be included in an employer-sponsored plan.
Initially, medical insurance was only for the employee and not the employee’s family. The growth in family coverage occurred following the 1949 Supreme Court ruling allowing benefits to become a part of labor negotiations and increasing the cost of medical insurance to employers. Medical (health) insurance cost escalation occurred in conjunction with the escalating cost of medical care to a point where executives found continued medical insurance price increases unsustainable. As a result, employers began to demand more for their money and their employees.
Executives pursued three lines of action to reduce escalating medical insurance costs. First, in the 1980s, they began shifting employer-sponsored insurance to managed care plans, which were developed to increase efficiency and cost controls of healthcare by combining financing, insurance, and service provision. Second, in the 1990s, employers demanded improved health outcomes, initiating the healthcare quality movement. Third, they began to require their employees to pay a portion of the premium and insisted upon other funding mechanisms such as copays and deductibles. After 1990, managed care plans became the dominant employer-sponsored insurance model. Limitations on patient choice in managed care led to a shift towards a hybrid approach. PPOs remain the most common type of employer-sponsored health plan. In 2025, 46% of covered workers were enrolled in a PPO, compared with 33% in a high-deductible health plan with a savings option, 12% in an HMO, and 9% in a POS plan (KFF, 2025).
Review webpage (KFF, 2025): Employer Health Benefits Survey 2025
Several factors influence employer-sponsored health insurance coverage. One of the most important is cost. As healthcare and insurance costs increase, both employers and employees face higher expenses, which can affect whether employers offer coverage and whether employees choose to enroll. Employers may also respond to rising costs by increasing employees’ share of premiums or other out-of-pocket costs (KFF, 2025).
Employment characteristics also affect access to employer-sponsored health insurance. Workers employed by smaller organizations, those earning lower wages, and part-time workers are less likely to have access to employer-sponsored health benefits than employees of larger organizations, higher-wage workers, and full-time workers (KFF, 2025). As a result, changes in the workforce and the types of jobs available can influence the number of people who have access to employer-sponsored coverage.
3.2.2 Individual (Non-Group) Insurance
Individual, or non-group, health insurance is coverage purchased by individuals and families rather than obtained through an employer or other group. Coverage may be purchased through the federal or a state Health Insurance Marketplace or directly from an insurance company. The individual market primarily serves people who do not have access to affordable employer-sponsored coverage and are not eligible for public programs such as Medicare or Medicaid. This may include self-employed individuals, workers whose employers do not offer health benefits, people between jobs, and individuals who retire before becoming eligible for Medicare.
Prior to implementation of the major insurance reforms of the Affordable Care Act (ACA), the individual insurance market offered fewer protections for consumers. Insurers could consider an applicant's health when determining eligibility or premiums in many states, exclude coverage for preexisting conditions, and offer plans that did not cover some services now required under the ACA. The ACA substantially changed the individual market by prohibiting insurers from denying coverage or charging higher premiums based on health status or preexisting conditions and requiring ACA-compliant individual plans to cover essential health benefits (HealthCare.gov, n.d.-b). The ACA also requires insurers in the individual and small-group markets to spend at least 80% of premium revenue on healthcare services and activities that improve healthcare quality or provide rebates to consumers when they do not meet that standard (CMS, n.d.-b).
The ACA also created Health Insurance Marketplaces where consumers can compare individual health plans and determine whether they qualify for financial assistance. In 2026, eligible consumers with household incomes between 100% and 400% of the federal poverty level may qualify for premium tax credits that reduce the amount they pay for Marketplace coverage. These tax credits are available only for coverage obtained through the Marketplace (HealthCare.gov, n.d.-f).
Marketplace enrollment increased substantially while the enhanced premium tax credits were available from 2021 through 2025. Those additional subsidies expired at the end of 2025, resulting in higher premium costs for many Marketplace enrollees in 2026. By February 2026, 19.2 million people had effectuated Marketplace coverage, compared with 21.8 million in 2025, a decline of approximately 12%. Despite the decline, Marketplace enrollment remained substantially higher than it was before the enhanced premium tax credits were introduced (Lo et al., 2026).
3.2.3 Managed Care
I. The Triple Aim
U.S. healthcare spending reached $5.3 trillion in 2024, or $15,474 per person, and accounted for 18.0% of the nation's gross domestic product (Centers for Medicare & Medicaid Services [CMS], 2026i). The Triple Aim (Fig. 3-1) provides a framework for simultaneously improving the patient experience of care, improving population health, and reducing the per capita cost of healthcare. The framework has since evolved into the Quintuple Aim, which adds healthcare workforce well-being and health equity to the original three aims (Institute for Healthcare Improvement [IHI], n.d.-b).
However, the U.S. stands out internationally for unusually high costs and poor outcomes among industrialized countries (Schneider et al., 2021). As a result, CMS was authorized to specify quality measures that would best advance the National Quality Strategy and build upon the Hospital Inpatient Quality Reporting infrastructure.
Figure 3-1
The Triple Aim
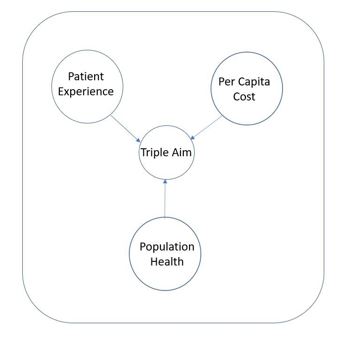
(Institute for Healthcare Improvement, n.d.-a)
II. Types of MCOs
Managed care organizations (MCOs) are integrated and coordinated organizations designed to provide care to a specific patient population. The main overarching goals are to keep costs down while providing high-quality patient care (Heaton & Tadi, 2020). There are four main types of MCOs: Health Maintenance Organization (HMO), Preferred Provider Organization (PPO), Point of Service (POS), and Exclusive Provider Organization (EPO).
Health maintenance organizations (HMOs)
Health maintenance organizations (HMOs) generally emphasize coordinated care delivered through an established provider network. HMOs usually limit coverage to physicians, hospitals, and other providers that participate in the plan, except for emergency care. Depending on the plan, members may select a primary care provider who coordinates their care and may need a referral before receiving certain specialty services (HealthCare.gov, n.d.-c). There are four common models of HMO organizations: group, independent practice association (IPA), network, and staff.
- Group Model - In the group model, the HMO contracts with a single, multispecialty entity for providers to provide care to its members. The HMO likely contracts additionally with a hospital in order to be able to provide comprehensive care to its members. The HMO pays the medical group a negotiated per capita rate, which the group distributes among its physicians, usually on a salaried basis.
- Independent Practice Association (IPA) Model - This set-up is closest to the original prepaid plans mentioned above. An IPA is a group of independent practitioners and group providers who decide to form a legal contract with a separate legal entity known as the IPA. This IPA then contracts with the HMO to negotiate the administrative and logistical details of any arrangement, as well as some of the financial risk. That is part of why this model is so appealing to providers (Gold, 1999).
- Network Model - In this model, the HMO contracts with multiple provider groups, either single or multispecialty, to provide services to its members.
- Staff Model - This model involves the HMO directly employing providers on a salary basis. Typically, the HMO employs physicians in a range of specialties in order to more fully serve its patients in its own facilities. HMOs often find this appealing because they exert a great deal of control directly over the physicians. This model is also known as a closed-panel HMO.
On the patient side, there are premiums, which are fees that must be paid on an annual or monthly basis. The premium enrolls the patient in the plan. A deductible is the amount an enrollee generally must pay for healthcare services that are subject to the deductible before the health plan begins paying its share of those costs. The next fee possibly encountered is the copay. The copay is a flat fee (e.g., $35 for every primary care visit) paid out of pocket by the patient for a set service. The final out-of-pocket expenditure is coinsurance. Coinsurance is a percentage of the remaining balance that the patient must pay (e.g., the HMO will pay 80% of the procedure, and the patient must pay the remaining 20%).
The HMO pays providers typically through salary or capitation. Capitation is when a fixed sum of money is paid per time unit (usually monthly) per patient being treated by the provider. For example, a physician in the HMO with 100 patients designating her as their Primary Care Provider would receive a fixed sum for each of those 100 patients each month.
Preferred provider organizations (PPOs)
Preferred provider organizations provide patients with quite a bit more choice. There is no gatekeeper in a PPO. The next difference is that there are different coverage tiers, with patients allowed to go in-network and out-of-network to providers and still receive insurance coverage. However, by going out-of-network, they would incur higher costs, such as higher deductibles or higher coinsurance rates. These features make PPOs open-panel plans. In an open panel plan, the MCO provides incentives for the patients to use participating (i.e., in-network) providers but also allows patients to use out-of-network providers.
PPOs generally negotiate discounted payment rates with participating healthcare providers rather than restricting coverage entirely to those providers. Prices for the same healthcare service can also vary among insurers, even when the service is provided by the same hospital (Craig et al., 2021).
Point of service (POS)
In the evolution of MCOs, point of service organizations are essentially trying to combine the cost-saving aspects of the HMOs with the increased flexibility of choice of provider in a PPO. Under this structure, the patient has a gatekeeper, usually a primary care provider, who is an initial point of service for the patient. The patient is also responsible for getting referrals to specialists from this gatekeeper.
Exclusive provider organizations (EPO)
Exclusive provider organizations are somewhat like HMOs in that they only pay for in-network costs, and all out-of-network costs are the patient's responsibility. However, unlike HMOs, they do not require a gatekeeper, and patients are not required to get referrals to see other in-network providers.
Table 2 A Comparison of Traditional MCOs
| Type of MCO | HMO | PPO | POS | EPO |
|---|---|---|---|---|
| Gatekeeper | X | X | ||
| Out-of-Pocket Costs are Patient's Responsibility | X | X |
(HealthCare.gov, n.d.-c)
III. Utilization Review
Utilization review (UR) is a process used by health plans and healthcare organizations to evaluate the medical necessity and appropriateness of healthcare services. UR may be used to manage healthcare utilization and costs while helping ensure that services are consistent with applicable clinical and coverage criteria (Giardino & Wadhwa, 2022). Utilization review can be required by hospitals, Workers’ Compensation, and insurance companies (Appelbaum & Parks, 2020; Bean et al., 2020; Siyarsarai et al., 2020). In addition to ensuring quality care, UR can be used to prevent fraud, waste, and inappropriate care from being provided to patients (Bean et al., 2020). There are three main types of utilization reviews:
- Prospective Utilization Review
- Concurrent Utilization Review
- Retrospective Utilization Review
When looking at these three types, the biggest difference in how they are conducted is when the review is done. Prospective UR, such as with prior authorization, is done prior to the medical services or procedures being delivered (Giardino & Wadhwa, 2022). Concurrent UR is conducted while the medical services are ongoing. Concurrent UR is often required by providers and can be used to validate the consumption of resources during a hospital stay, such as for inpatient case management where continuous review is necessary (Namburi & Tadi, 2022; Olakunle et al., 2011). It is also frequently associated with discharge planning to help ensure continuity of care (Smith et al., 2020). Finally, retrospective UR is done after the services are provided and the bill is delivered (Giardino & Wadhwa, 2022).
While there are some differences between these three methods because of when they are conducted, there are many similarities between the basic procedures of these three approaches. The first step is to check eligibility with the insurance plan and/or ensure that the requested service is appropriate. If checking for appropriateness, typically, the insurer or plan will use nationally developed clinical guidelines for standards of care (Giardino & Wadhwa, 2022). The next step is to gather clinical information to determine if the criteria are met for the service. The clinical staff must document everything, including the absence of things, for this step to succeed. It may be common for clinical staff to fail to note things that look normal (i.e., “charting by exception”), but this can result in denials and delays during the UR process and is strongly discouraged. The provider will be notified if the reviewer determines that the criteria are met. If not, the provider and the patient will be notified of the denial, and they can appeal, usually by providing more information.
