
4.3 Quality of Care
Sections:
4.3.1 Definition and Domains of Quality
The Institute of Medicine identified six aims for a high-quality healthcare system that continue to provide a widely used framework for evaluating healthcare quality (AHRQ, 2020b):
- Safe: Avoiding harm to patients from the care intended to help them.
- Effective: Providing services based on scientific knowledge to all who could benefit and refraining from providing services to those not likely to benefit (i.e., avoiding underuse and misuse).
- Patient-centered: Providing care that is respectful of and responsive to individual patient preferences, needs, and values and ensuring that patient values guide all clinical decisions.
- Timely: Reducing waits and sometimes harmful delays for both those who receive and those who provide care.
- Efficient: Avoiding waste, including waste of equipment, supplies, ideas, and energy.
- Equitable: Providing care that does not vary in quality because of personal characteristics such as gender, ethnicity, geographic location, and socioeconomic status.
This framework continues to guide quality improvement initiatives across America’s healthcare system. The evidence-based practice (EBP) movement began with the public acknowledgment of unacceptable patient outcomes resulting from a gap between research findings and actual healthcare practices. For EBP to be successfully adopted and sustained, it must be adopted by healthcare team members, system leaders, and policymakers. Regulations and recognition are also necessary to promote the adoption of EBP. For example, the Magnet Recognition Program promotes nursing as a leader in catalyzing the adoption of EBP and using it as a marker of excellence (Stevens, 2013).
4.3.2 Quality Improvement Methods
Healthcare organizations use a variety of quality improvement methodologies to identify problems, redesign processes, reduce variation and waste, and improve patient outcomes. Four commonly used approaches are Plan-Do-Study-Act (PDSA), Six Sigma, Lean, and Lean Six Sigma.
I. Plan-Do-Study-Act
One of the most commonly used improvement methods is the Plan-Do-Study-Act (PDSA) cycle (Fig. 4-3). Since quality improvement projects are typically team-based, PDSA places great emphasis on including the right people for success (Langley et al., 2009). Planning can be the most important part of a successful project. Change should be monitored and adjusted as needed. The cycle of PDSA allows for refinement of the change to implementation on a broader scale after successful changes have been identified (Langley et al., 2009). The following two documents review the steps associated with each phase of the PDSA cycle and examples in a healthcare setting:
- The PDSA Cycle Step by Step (Administration for Children & Families, 2018)
- Plan-Do-Study-Act (PDSA) Directions and Examples (AHRQ, 2020c)
Figure 4-3
Plan-Do-Study-Act Method for Quality Improvement
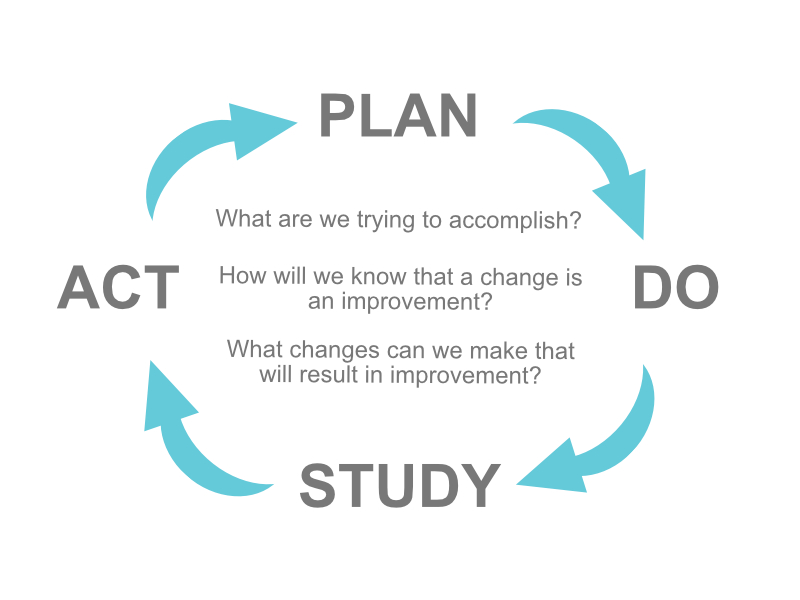
(AHRQ, 2020c)
II. Six Sigma
Six Sigma is another model for quality improvement using a measurement-based strategy for process improvement and problem reduction applied to improvement projects. The term Six Sigma derives from the Greek letter σ (sigma), used to denote standard deviation from the mean or how far something deviates from perfection. A Six Sigma process is commonly associated with a performance level of approximately 3.4 defects per million opportunities (American Society for Quality, 2023a). Six Sigma models include DMAIC (define, measure, analyze, improve, control) and DMADV (define, measure, analyze, design, verify). DMAIC is generally used to improve an existing process, whereas DMADV is used to design a new process or substantially redesign an existing one (American Society for Quality, n.d.-a). DMAIC is a formalized problem-solving method designed to improve the effectiveness and ultimate efficiency of the organization (Table 1).
Table 1 The DMAIC Method
| What is DMAIC? | |
|---|---|
| Define: What is the problem? |
Who wants the project, and why The scope of the project/improvement Key team members and resources for the project Critical milestones and stakeholder review Budget allocation |
| Measure: How big is the problem? |
Ensure measurement system reliability Prepare a data collection plan How many data points need to be collected How much time will data collection take What is the sampling strategy Who will collect data, and how will it be stored |
| Analyze: What is causing the problem? |
Use a variety of tools Choose the tools that best fit the improvement strategy |
| Improve: What will solve the problem? |
Gain insight into the problem's causes Control/eliminate those causes to achieve better performance |
| Control: How can the improvement be sustained? |
The best controls are those that require no monitoring |
(Ahmed, 2019)
Having arrived at one or more solutions, it is time to implement new processes or systems and monitor to ensure consistent achievement. The “control” stage is the release of responsibility from the project. Once this stage is achieved, some organizations may implement the support of a Six Sigma project team to ensure the sustainability of the improvement in the future.
III. Lean
According to Simon (2013), the three key pillars of Lean in healthcare include (Fig. 4-4):
- Delivering value (from the patient's perspective)
- Eliminating waste (from the patient's perspective)
- Continuously improving processes to better serve patients
Figure 4-4
The Three Key Pillars of Lean in Healthcare

(Simon, 2013)
Lean methodology identifies eight common forms of waste: defects, overproduction, waiting, non-utilized talent, transportation, inventory, motion, and extra-processing (American Society for Quality, n.d.-b). Some examples that may seem insignificant include the following:
- Reducing inventory, especially medical supplies that have expiration dates
- Reducing or maximizing the use of space
- Reducing wait times
- Reductions of defects, medical errors, and mistakes
- Increasing the overall productivity and utilization of employees
Value stream mapping (VSM) is commonly used in Lean improvement efforts to examine how work moves through a process from beginning to end. It helps teams visualize the current process and identify areas where delays, unnecessary steps, or other forms of waste may occur (American Society for Quality, 2023b).
Using Lean concepts can improve the quality of patient care. To illustrate, review these Lean implementation case studies (Purdue University, 2022):
Rural hospital uses Lean Daily Improvement to increase patient feedback
Primary care practice improves EHR efficiency for better physician-patient interaction
Also, consider these various scenarios:
- Providers walk down the hall to a printer. This effort is wasted motion and time. A more efficient solution may be to install a printer at both ends of the clinic.
- The new electronic health record (EHR) system is not optimized, and physicians must scroll through hundreds of diagnosis and billing codes. Consider condensing the list of available codes to the top five or ten. This small change could save them a significant amount of time and frustration.
- A nurse performing clerical duties may need to redistribute some tasks to non-licensed employees, thus optimizing their nursing skills on more appropriate tasks.
- One floor is short-staffed, while another floor has a low patient volume. Nursing staff may need to be redistributed to help balance the workload on the other floors.
IV. Lean Six Sigma
Lean Six Sigma combines Lean's emphasis on reducing waste and improving process flow with Six Sigma's emphasis on reducing variation and defects. The combined approach uses tools from both methodologies to improve the efficiency, consistency, and quality of organizational processes.
Successful implementation of Lean and Six Sigma requires clear goals, effective communication, leadership support, employee engagement, and a willingness to test and refine changes. Identifying respected clinicians or staff members who can serve as change champions may also help build support for improvement initiatives.
4.3.3 Measures of Quality
Approaches used to assess, promote, and improve healthcare quality include:
- Magnet Recognition Program
- Value-based reimbursement models
- CMS quality initiatives
- Accreditation review process
- Quality measures
- National Performance Goals
I. Magnet Recognition Program
The Magnet Recognition Program recognizes healthcare organizations that demonstrate nursing excellence and align nursing leadership and practice with improved patient outcomes. Magnet-designated organizations emphasize professional development, nursing leadership, and organizational support for high-quality patient care (American Nurses Association, n.d.).
II. Reimbursement Models
Value-based reimbursement models link healthcare payments to measures of quality, outcomes, efficiency, or performance rather than relying solely on the volume of services provided. These models use financial incentives and payment adjustments to encourage healthcare organizations and providers to improve quality and patient outcomes. These reimbursement models directly impact the evidence-based care nurses provide at the bedside, and the associated documentation of assessments, interventions, and nursing care plans to ensure quality performance criteria are met.
CMS identifies five programs as its original value-based programs, which link provider performance on quality measures to Medicare payment (Centers for Medicare & Medicaid Services [CMS], 2026e).
- End-Stage Renal Disease Quality Incentive Program - CMS administers the End-Stage Renal Disease Quality Incentive Program to promote high-quality services in renal dialysis facilities. The first of its kind in Medicare, this program changes the way CMS pays for the treatment of patients who receive dialysis by linking a portion of payment directly to facilities’ performance on quality of care measures.
- Hospital Value-Based Purchasing Program - The Hospital Value-Based Purchasing Program (VBP) rewards acute care hospitals with incentive payments for the quality of care provided in the inpatient hospital setting. The Hospital VBP Program encourages hospitals to improve the quality, efficiency, patient experience, and safety of care that Medicare beneficiaries receive during acute care inpatient stays.
- Hospital Readmission Reduction Program - The Hospital Readmission Reduction Program is a Medicare value-based purchasing program that encourages hospitals to improve communication and care coordination to better engage patients and caregivers in discharge plans and, in turn, reduce avoidable readmissions.
- Value Modifier Program (also called the Physician Value-Based Modifier) - The Merit-based Incentive Payment System (MIPS) under the Quality Payment Program replaced the Physician Feedback/Value-Based Payment Modifier Program on January 1, 2019. The Physician Feedback Program provided comparative performance information to solo practitioners and medical practice groups, as part of Medicare’s efforts to improve the quality and efficiency of medical care furnished to Medicare beneficiaries.
- Hospital-Acquired Condition Reduction Program - The Hospital-Acquired Condition Reduction Program encourages hospitals to improve patient safety and reduce hospital-acquired conditions by linking Medicare payment to performance on designated quality measures.
Other value-based programs include (CMS, 2026e):
- Skilled Nursing Facility Value-Based Purchasing (SNF VBP) Program – The SNF VBP Program links Medicare payments to skilled nursing facility performance on designated quality measures. CMS withholds a portion of Medicare fee-for-service Part A payments to participating SNFs and redistributes a portion of those funds as incentive payments based on each facility’s performance. The program is intended to encourage better quality and outcomes for Medicare beneficiaries receiving skilled nursing facility care (CMS, 2026d).
- Expanded Home Health Value-Based Purchasing (HHVBP) Model – The expanded HHVBP Model applies to Medicare-certified home health agencies nationwide and links Medicare fee-for-service payment adjustments to performance on a set of quality measures. The expanded model began in 2022, with the first performance year in 2023 and the first payment adjustments occurring in 2025. The model is designed to improve the quality and efficiency of home health care and patient outcomes (CMS, n.d.).
III. CMS Quality Initiatives
The Centers for Medicare & Medicaid Services (CMS) establishes quality initiatives focusing on several key quality measures of healthcare. These quality measures provide a comprehensive understanding and evaluation of the care an organization delivers, and responses from the patients who received care. These quality measures evaluate many areas of healthcare, including the following (CMS, 2026c):
- Health outcomes
- Clinical processes
- Patient safety
- Efficient use of healthcare resources
- Care coordination
- Patient engagement in their own care
- Patient perceptions of their care
These measures of quality focus on providing the care the patient needs when the patient needs it in an affordable, safe, and effective manner. It also means engaging and involving the patient, so they take ownership of their care at home. CMS administers quality programs across multiple healthcare settings. These programs use approaches such as quality reporting, public reporting, payment incentives, and payment adjustments to encourage improvements in healthcare quality (CMS, 2025). The following CMS website provides links to specific examples of quality reporting and value-based payment programs and initiatives (CMS, 2025): CMS Quality Reporting and Value-Based Programs & Initiatives
IV. Accreditation
Healthcare organizations may seek accreditation from external organizations that evaluate compliance with established quality and safety standards. The accrediting organization varies by healthcare setting and type of organization. Examples include The Joint Commission, the National Committee for Quality Assurance (NCQA), and other accrediting organizations recognized for specific healthcare settings or services.
V. Quality Measures
Quality measures are tools used to assess healthcare processes, outcomes, patient experiences, and organizational performance. CMS uses quality measures across multiple quality improvement, public reporting, and payment programs. Accrediting organizations may also incorporate quality measures into their standards and performance requirements (CMS, 2026c).
VI. National Performance Goals
National Performance Goals (NPGs) are Joint Commission requirements designed to focus attention on high-priority areas of healthcare safety, quality, and performance. Effective January 1, 2026, The Joint Commission replaced the former National Patient Safety Goals with National Performance Goals. The NPGs organize existing Joint Commission requirements into measurable, actionable topics intended to help organizations improve patient safety and quality. The goals address areas such as correct patient identification and care, culture of safety, emergency readiness, infection prevention and control, pain management, and safe, informed care (The Joint Commission, 2026).
